|
Updated September 3, 2026
It's easy to become angry when living with chronic pain. I've even heard the term “paingry” used to describe it. Anger may be directed toward ourselves, our circumstances, healthcare providers, family members, or other people. Anger is a normal human emotion. It can sometimes be helpful and motivate us to address problems. But when anger becomes intense, persistent, or difficult to control, it can increase distress and interfere with relationships, functioning, and quality of life. Anger and chronic pain Research suggests that anger can be particularly important in chronic pain. A 2026 study of 735 adults seeking treatment for chronic pain identified different patterns of anger and perceived injustice. People with higher levels of anger and perceived injustice had more severe pain-related outcomes, both at the initial assessment and at follow-up about five months later. These findings show an association rather than proving that anger causes worse pain, but they highlight the importance of recognizing and addressing anger as part of chronic pain care. Anger can also become part of a cycle. Pain can lead to frustration and anger. Anger can increase stress and distress. And increased distress can make it harder to respond to pain in helpful ways. The goal isn't to eliminate anger. It's to learn how to recognize it and respond differently. How to manage anger
What about perceived injustice? Chronic pain can sometimes create a strong sense that life isn't fair. “Why me?” “The doctors should have fixed this.” “Other people don't understand.” These thoughts are understandable. Sometimes people really have experienced poor care, unfair treatment, or circumstances that shouldn't have happened. But repeatedly dwelling on injustice may keep anger alive and make it harder to move forward. The 2026 study mentioned above found that higher perceived injustice, particularly when combined with higher levels of anger, was associated with the most severe pain outcomes. The goal isn't to deny injustice. It's to recognize when dwelling on it no longer helps. Don't let anger take control You don't have to eliminate anger. You can't control everything that happens around you, and there will be times when anger is a completely understandable response. But you can learn to control how you respond. Recognize the anger. Understand what's behind it. Pause before reacting. Challenge unhelpful thoughts. Then choose how you want to respond. Anger is something you experience. It doesn't have to control what you think, say, or do. I explore the role of emotions, cognitive restructuring, and other strategies for managing chronic pain in my book, Trapped by Chronic Pain? Break Free and Take Back Your Life. Learn more Updated September 3, 2026 Has your doctor referred you to pain management, but you're unsure where to go or what to expect? With names such as pain clinics, pain centers, pain management centers, pain treatment centers, pain institutes, pain management programs, and pain rehabilitation programs, it's easy to get confused. The problem is that these names don't necessarily tell you what kind of care you'll receive. I've tried to separate the different types of pain services below into broad categories based on their approach, level of collaboration, and treatment focus. Keep in mind that real-world programs don't always fit neatly into one category, and some facilities combine elements of several approaches. Interventional pain management Interventional pain management is typically physician-led and often focuses on identifying and treating specific pain conditions, reducing pain, and improving function. Depending on the facility and the patient's condition, treatment may include medications, injections, nerve blocks, radiofrequency procedures, spinal procedures, neuromodulation such as spinal cord stimulation, or other interventions. Some centers may also offer or coordinate complementary treatments or surgical consultations. These treatments can be appropriate for selected patients and conditions. However, interventional treatments are often focused primarily on reducing symptoms or treating a specific pain generator rather than providing a comprehensive rehabilitation program. Multidisciplinary pain management Multidisciplinary pain management brings together professionals from different disciplines to provide a range of treatments. A patient might receive medication management from a physician, physical therapy from a physical therapist, and psychological treatment from a psychologist. These services may be available within the same organization or through referrals, but the providers may work relatively independently, with each discipline maintaining its own treatment goals and approach. In other words, you may have access to multiple disciplines without necessarily having those disciplines work closely together. Multidisciplinary pain rehabilitation Multidisciplinary pain rehabilitation brings together multiple healthcare disciplines, with a primary focus on restoring function and improving quality of life rather than simply eliminating pain. Programs may include physical therapy, occupational therapy, psychology, rehabilitation medicine, nursing, medication management, education, relaxation training, and other services. These programs are often more comprehensive than conventional pain management and may last several weeks. However, the degree of communication and coordination among providers can vary from one program to another. Interdisciplinary pain rehabilitation Interdisciplinary pain rehabilitation takes collaboration a step further. An interdisciplinary team works together using a shared biopsychosocial approach, common treatment goals, and a coordinated plan. Rather than receiving a series of separate treatments from different providers, the team communicates and works toward a common goal with the patient. The team may include physicians, psychologists, physical therapists, occupational therapists, nurses, pharmacists, dietitians, and other professionals, depending on the program. The focus is generally on helping people develop the skills and confidence to actively manage chronic pain and improve their ability to function. Treatment may include:
Programs are often intensive and may be group-based. Some hospital-based programs involve several hours of treatment each day for several weeks. The goal isn't simply to reduce pain. It's to help the person return to meaningful activities, improve physical and emotional functioning, reduce fear and avoidance, and become more confident in managing pain. This approach closely resembles the program I attended at Mayo Clinic. Mayo describes its Pain Rehabilitation Center as an integrated, team-based program that involves pain medicine, physical therapy, psychology, occupational therapy, biofeedback, and nursing, with a focus on self-management, physical reconditioning, medication management, and quality-of-life improvement. Why does the difference matter? When someone is referred to "pain management," it's reasonable to ask what that actually means. Will you primarily receive medications and procedures? Will you see several different specialists who work independently? Or will you participate in a coordinated rehabilitation program in which the team works together toward shared goals? None of these approaches is automatically right or wrong for everyone. The appropriate approach depends on the type of pain, the individual's medical situation, goals, and available treatment options. But for persistent chronic pain, particularly when pain has significantly affected physical function, emotional well-being, work, relationships, or quality of life — a comprehensive rehabilitation approach may offer something that a procedure-focused model can't: an opportunity to learn skills for managing pain over the long term. Active vs. passive pain management As pain becomes persistent, treatments aimed solely at reducing pain may not be enough. Medications, injections, procedures, and other symptom-focused treatments can have a role in appropriate circumstances. But they generally work best when they're part of a broader treatment plan that also helps the person become more active and develop self-management skills. The goal isn't to eliminate every passive treatment. The goal is to avoid becoming dependent on passive treatments as the only way to manage pain. An active self-management approach can help people develop the knowledge, skills, confidence, and physical capacity to take a more active role in managing their pain and their lives. My experience at Mayo Clinic It was my family doctor and a local surgeon who recommended that I attend the three-week outpatient Mayo Clinic Pain Rehabilitation Center rather than undergo another risky surgery in an attempt to fix my pain. The program changed my life. One of the most valuable parts of the experience was that I wasn't simply given another treatment and sent home. I learned how to approach pain differently. I worked with a team that addressed the physical, psychological, behavioral, and medical aspects of chronic pain. I learned about pain, participated in physical reconditioning, developed coping and self-management skills, and learned how my thoughts, emotions, behaviors, and activity levels could influence my experience of pain. Another important part of the program was social modeling—seeing other people with similar pain experiences work through the same challenges and develop the skills they needed to move forward. Mayo's current program continues to emphasize an integrated team approach, physical reconditioning, behavioral strategies, medication optimization, and support for people to shift toward greater self-management and a more active life. Conclusions and thoughts There isn't a single universal definition of “pain management,” and programs can differ considerably in their treatment philosophies, organization, and goals. When you're referred to pain management, don't be afraid to ask questions:
A comprehensive interdisciplinary pain rehabilitation program may not be the right choice for everyone. These programs can also be demanding, requiring a significant time commitment and active participation. But if you're living with persistent pain that has taken over your life, rehabilitation may offer something different from simply trying the next medication, procedure, or surgery. It can teach you skills that you can continue using long after the program ends. A final thought I believe the most important distinction isn't whether a program is called a pain clinic, pain center, pain management program, or pain rehabilitation program. It's this: Are you being given another treatment for your pain or are you also being given the tools and skills to manage your pain and take back your life? For me, learning to actively manage my chronic pain was a turning point. Please discuss your medical situation and treatment options with your healthcare team. Learn more
 Updated September 4, 2026 I was blessed to see Nik Wallenda, the famous high-wire performer, perform while I was on vacation. As impressive as Nik's balancing skills were, the message he shared about fear, persistence, and moving forward was even more impressive. Fear can hold us back. In 2017, Nik was involved in a rehearsal accident while performing an eight-person pyramid on a high wire. Five performers fell about 25 feet and were injured. Nik was on the wire but did not fall. (upi.com) The experience was serious enough that Nik considered giving up high-wire performing. But he didn't. That got me thinking about fear and chronic pain. Fear can be protective. It helps us recognize danger and avoid situations that could cause harm. But fear can also become a problem when it causes us to avoid activities that are actually safe. Fear of pain can become a cycle When pain has been present for a long time, it's understandable to become afraid of making it worse. That fear can lead to avoiding movement, exercise, activities, or situations that have become associated with pain. Avoidance may provide short-term relief from fear or distress. But over time, it can contribute to reduced activity, loss of confidence, disability, and a smaller life. This is an important part of the fear-avoidance model of chronic pain. Research has consistently found an association between greater pain-related fear and disability. The problem isn't the existence of fear. The problem is when fear starts making decisions for us. Learn to manage fear The answer isn't to ignore fear or push through everything. Instead, learn to recognize the difference between a genuine warning sign and fear based on the expectation that movement or activity will automatically cause harm. For some people, gradually approaching activities they have avoided out of fear can help build confidence and offer new experiences that challenge those expectations. This is the basic principle behind graded exposure. You don't have to wait until fear disappears before taking action. You can take a small step while fear is still present. Then another. And another. Over time, those experiences can help change what you believe you're capable of doing. Keep moving forward Watching Nik Wallenda reminded me that courage isn't the absence of fear. It's the willingness to move forward despite fear when doing so is safe and meaningful. The same can apply when living with chronic pain. You may be afraid that an activity will increase pain. You may be afraid of making things worse. You may have avoided something for so long that returning to it feels overwhelming. Start small. Choose something meaningful. Challenge the fear gradually and safely. And learn from what happens. Pain doesn't always mean harm, and fear doesn't always mean stop. Sometimes the next step is simply learning that you can do more than fear has led you to believe. Don't let fear make your life smaller than it needs to be. Watch the 2017 rehearsal accident involving Nik Wallenda and the eight-person pyramid. Related resources
Updated September 4, 2026
Chronic pain can affect much more than the body. It can influence thoughts, emotions, relationships, activities, and the way we see the future. Anger, resentment, frustration, and a sense of injustice can become part of the experience. At the same time, gratitude and forgiveness may offer opportunities to change how we respond to those emotions. They aren't magic cures for pain. But they may help reduce distress and suffering, improve well-being, and change the role pain plays in our lives. Forgiveness Living with chronic pain can sometimes leave us angry about what happened. Maybe an injury changed life unexpectedly. Maybe a medical treatment didn't work. Maybe something was missed or handled poorly. Maybe life simply feels unfair. I experienced that sense of injustice myself. Forgiveness doesn't mean that what happened was okay. It doesn't mean forgetting, excusing harmful behavior, giving up accountability, or reconciling with someone who hurt you. Forgiveness can mean letting go of some of the anger, resentment, and bitterness associated with what happened. Research on forgiveness and chronic pain is still limited, but a systematic review found that five of seven studies reviewed showed an association between lower forgiveness and either greater pain experience or lower pain tolerance. The authors concluded that more research is needed to determine whether forgiveness can be an effective intervention for chronic pain. (PubMed) The important question may not be: "Was what happened fair?" It may be: "Is continuing to carry this anger helping me move forward?" Sometimes letting go is less about changing what happened and more about changing what happens next. Gratitude Gratitude doesn't mean pretending everything is good. It doesn't mean ignoring difficult circumstances or telling yourself that you should be grateful because someone else has it worse. Gratitude means deliberately noticing and appreciating the things that are meaningful, helpful, or positive in life. Even when chronic pain is present, there may still be people, relationships, experiences, abilities, or moments worth appreciating. Research on gratitude interventions in the general population has found improvements in gratitude, mental health, anxiety, depression, life satisfaction, and positive mood, although the certainty of some findings is limited. (PMC) More recent research specifically examining fibromyalgia is also encouraging. A 2025 systematic review found that higher gratitude was associated with better quality of life, well-being, and some pain-related outcomes, but the authors emphasized that more research is needed before gratitude can be considered an established treatment. (PMC) Gratitude isn't about denying what is difficult. It's about making sure the difficult things don't become the only things that receive attention. Change the emotional experience Forgiveness and gratitude are two ways of changing how we respond emotionally to difficult circumstances. They don't require pretending that everything is okay. They require recognizing what we're feeling and deciding whether holding on to certain emotions is helping us or keeping us stuck. For me, learning to let go of some anger and resentment helped me move forward. Practicing gratitude helped me notice that chronic pain wasn't the only thing happening in my life. There were still people to love. Things to experience. Activities to enjoy. Goals to pursue. And reasons to be thankful. Try it yourself Consider starting with something simple. For forgiveness: Think about something that continues to generate anger or resentment. Ask yourself whether holding on to those emotions is helping you move forward. Forgiveness doesn't require forgetting or excusing what happened. It may simply mean choosing not to let the past continue to control the present. For gratitude: At the end of each day, identify three things you appreciated. They don't have to be significant. A conversation with someone you care about. A good meal. A beautiful day. A favorite song. A laugh. A walk.A good night's sleep. A moment when you accomplished something you didn't think you could do. The purpose isn't to convince yourself that life is perfect. It's to deliberately notice that life contains more than pain and problems. Let go and move forward Forgiveness and gratitude won't magically make chronic pain disappear. But they may help change how we experience difficult circumstances and how much attention we give them. Forgiveness can help us loosen the grip of anger and resentment. Gratitude can help us notice what remains meaningful and worthwhile. Neither requires denying reality. Both can help create space for something beyond pain. You don't have to forget the past to move forward. And you don't have to wait for everything to be perfect before finding something to appreciate. Sometimes moving forward begins with letting go of what no longer helps and making room for what does. Learn more about forgiveness
Learn more about gratitude
Learn more about anger management
Learn more about stress reduction Updated September 4, 2026 Our thoughts, emotions, and behaviors can influence how we experience and respond to pain. Cognitive Behavioral Therapy (CBT) is a form of psychological treatment that can help people identify unhelpful thoughts and behaviors, develop more effective coping strategies, and become more active in managing chronic pain. CBT doesn't mean that pain is "all in your head." The pain is real. Instead, CBT recognizes that pain is a complex biopsychosocial experience and that the way we think, feel, and behave can influence how we respond to pain and how much it affects our lives. How can CBT help? CBT is based on the idea that thoughts, emotions, behaviors, and pain can influence one another. When living with chronic pain, it's easy to become caught in unhelpful patterns. You may begin thinking:
Those thoughts can affect emotions and behavior. They may contribute to fear, avoidance, inactivity, frustration, or loss of confidence. CBT can help identify these patterns and develop more helpful ways of thinking and responding. The goal isn't to think just positively. It's about thinking more accurately and responding more effectively. CBT is about skills CBT can provide practical skills that you can continue using long after you've learned them. These may include:
These skills can help change the role pain plays in your life. CBT isn't about eliminating every unpleasant thought or emotion. It's about learning that thoughts are not always facts and that emotions don't have to determine what you do. CBT and self-management One of the things I value most about CBT is that it gives people tools they can use themselves. A therapist may teach you the skills, help you identify patterns, and provide guidance as you practice them. Over time, however, those skills can become part of your own self-management toolkit. That's important because chronic pain doesn't disappear when an appointment ends. You need strategies that you can use at home, at work, with family, and while doing the activities that matter to you. CBT can be one part of that toolkit. It isn't a cure for pain CBT isn't a magical cure for chronic pain. It doesn't mean pain is imaginary, and it doesn't guarantee it will disappear. The goal is broader than pain reduction. CBT can help people change how they respond to pain, reduce the impact of unhelpful thoughts and behaviors, improve coping and confidence, and work toward greater function and quality of life. Research supports CBT and other psychological approaches as useful components of chronic pain management, although the size of benefit varies among conditions and individuals. My experience I learned CBT while attending the three-week interdisciplinary Mayo Clinic Pain Rehabilitation Center. It changed my pain experience and my life by giving me practical tools to:
CBT didn't make my chronic pain disappear. It helped me change my relationship with pain and how I responded to it. That distinction was important. Find a therapist trained in CBT for chronic pain It can be difficult to find a psychologist or other mental health professional with specific training and experience in CBT for chronic pain. When looking for a therapist, ask about their experience working with people who have chronic pain and how they approach treatment. You may also want to ask how they incorporate pain education, cognitive restructuring, activity, goal setting, and self-management into their work. You can find search tools here:
Learn more and do more
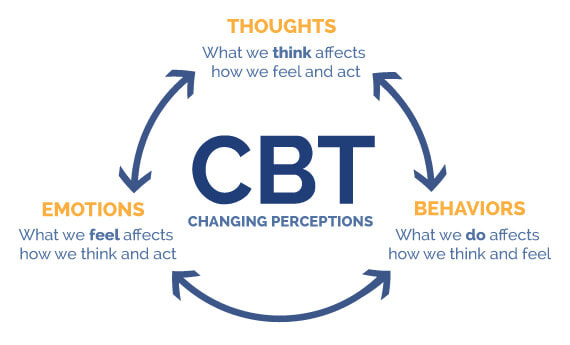 Image courtesy of McGovern Medical School
|