|
Updated September 3, 2026
It's important to remember that you're not alone. There are strategies and skills that can help you develop greater control over how you respond to chronic pain, reduce its impact on daily life, and live well despite it. Changing how you think about pain, how you respond emotionally, and how you behave in its presence can influence the pain experience and, importantly, how much pain affects your activities, relationships, and quality of life. Self-management doesn't mean giving up appropriate medical care. It means making self-management part of the treatment rather than relying on treatment to do everything for you. IASP identifies active cognitive and behavioral strategies, physical activity, emotional coping, healthy lifestyle behaviors, and appropriate use of healthcare resources as important components of chronic pain self-management. My experience My journey took a turn for the better when I accepted the reality that pain was part of my life, stopped the relentless pursuit of a single cause or cure, and discovered the power of self-management through a structured interdisciplinary pain rehabilitation program. Acceptance didn't mean giving up. It meant changing my goal. Instead of making the elimination of pain a requirement for moving forward, I began focusing on what I could do to improve my life. I learned to change how I thought about pain, how I responded to it, and how I behaved when pain was present. That shift gave me a greater sense of control over how I lived my life. You have more influence than you may think You can't control everything about pain. You can't always control when it appears, how intense it feels, or what caused it. But there are things you can influence:
These changes won't necessarily eliminate pain, and they won't work the same way for everyone. But they can change the relationship with pain and reduce the impact it has on daily life. Self-management programs are designed to build confidence and practical skills for managing pain and its consequences. The goal is to live, not just to treat For years, I focused on finding the next treatment that might finally make the pain go away. Pain rehabilitation taught me to think differently. The goal wasn't simply to find another treatment. The goal was to develop the skills and confidence to live a meaningful life while managing chronic pain. That distinction changed everything for me. You may not be able to control every aspect of the pain experience. But you can learn to influence how you think, feel, and behave in response to it. And those changes can make a meaningful difference in how you live. You can change the pain experience. And you can change the role pain plays in your life. Learn more
Updated September 3, 2026
“In a word, describe how you feel right now.” I recently saw this question asked in a fibromyalgia support group with nearly 100,000 members. Almost all of the 377 responses posted within two days had negative connotations. People described themselves as exhausted, defeated, overwhelmed, afraid, lousy, anxious, depressed, painful, lifeless, restricted, broken, irritable, lost, done, and disconnected. A few positive words appeared, including confident, grateful, proud, and hopeful. Reading those responses saddened me. Not because people with chronic pain shouldn't feel exhausted, afraid, frustrated, or overwhelmed. Those feelings are understandable when you're living with persistent pain. What struck me was how completely pain seemed to be dominating the emotional landscape for so many people. When pain starts to take over Chronic pain can gradually affect much more than how your body feels. It can influence your thoughts, emotions, behavior, relationships, activities, work, sleep, and expectations for the future. Over time, your life can become increasingly organized around pain—what you can do, what you can't do, what might make it worse, and what treatment might finally make it go away. Pain can become the center of your attention. And when that happens, it's easy for your identity and your life to become defined by pain rather than by the things that matter to you. I know because I've been there. My answer to the question was confident. But there was a time in my journey with chronic pain when my answer wouldn't have been nearly as positive. What changed for me? Things began to change after I attended a pain rehabilitation program. I learned that living well with chronic pain doesn't necessarily require waiting for the pain to disappear first. I learned to accept that pain was part of my life without allowing it to define my life. I also learned active self-management strategies that helped me change how I thought about, responded to, and behaved around pain. That didn't mean ignoring my pain or pretending it wasn't real. It meant learning that I could still do meaningful things even when pain was present. Over time, my focus shifted from “How can I get rid of my pain?” to “How can I live the life I want while managing my pain?” That was a profound change. Chronic pain isn't prolonged acute pain One of the most important lessons I learned is that chronic pain shouldn't simply be treated as acute pain that has lasted too long. Persistent pain can involve different biological, psychological, and social factors than acute pain. The goal of treatment also may need to change. Instead of endlessly searching for something to find and fix, treatment can also focus on helping people understand their pain, improve function, build confidence, reduce fear and avoidance, and develop skills for self-management. That doesn't mean abandoning medical treatment. It means expanding the goal beyond simply trying to make the pain disappear. From pain-centered to life-centered People living with chronic pain don't need to feel positive all the time. They don't need to deny their pain, suppress difficult emotions, or pretend everything is okay. But pain doesn't have to occupy the center of every part of life. There can still be room for relationships, hobbies, work, movement, laughter, purpose, and hope. For me, pain rehabilitation helped me make that shift. My pain didn't have to disappear before I could begin living again. I learned to stop making my life revolve around pain and start making pain fit into my life. That's the difference active self-management made for me. And it's one reason I believe clinicians should look beyond simply finding something to fix and help people develop the knowledge, skills, and confidence they need to manage persistent pain and live meaningful lives. Learn more
Updated September 3, 2026 Has your doctor referred you to pain management, but you're unsure where to go or what to expect? With names such as pain clinics, pain centers, pain management centers, pain treatment centers, pain institutes, pain management programs, and pain rehabilitation programs, it's easy to get confused. The problem is that these names don't necessarily tell you what kind of care you'll receive. I've tried to separate the different types of pain services below into broad categories based on their approach, level of collaboration, and treatment focus. Keep in mind that real-world programs don't always fit neatly into one category, and some facilities combine elements of several approaches. Interventional pain management Interventional pain management is typically physician-led and often focuses on identifying and treating specific pain conditions, reducing pain, and improving function. Depending on the facility and the patient's condition, treatment may include medications, injections, nerve blocks, radiofrequency procedures, spinal procedures, neuromodulation such as spinal cord stimulation, or other interventions. Some centers may also offer or coordinate complementary treatments or surgical consultations. These treatments can be appropriate for selected patients and conditions. However, interventional treatments are often focused primarily on reducing symptoms or treating a specific pain generator rather than providing a comprehensive rehabilitation program. Multidisciplinary pain management Multidisciplinary pain management brings together professionals from different disciplines to provide a range of treatments. A patient might receive medication management from a physician, physical therapy from a physical therapist, and psychological treatment from a psychologist. These services may be available within the same organization or through referrals, but the providers may work relatively independently, with each discipline maintaining its own treatment goals and approach. In other words, you may have access to multiple disciplines without necessarily having those disciplines work closely together. Multidisciplinary pain rehabilitation Multidisciplinary pain rehabilitation brings together multiple healthcare disciplines, with a primary focus on restoring function and improving quality of life rather than simply eliminating pain. Programs may include physical therapy, occupational therapy, psychology, rehabilitation medicine, nursing, medication management, education, relaxation training, and other services. These programs are often more comprehensive than conventional pain management and may last several weeks. However, the degree of communication and coordination among providers can vary from one program to another. Interdisciplinary pain rehabilitation Interdisciplinary pain rehabilitation takes collaboration a step further. An interdisciplinary team works together using a shared biopsychosocial approach, common treatment goals, and a coordinated plan. Rather than receiving a series of separate treatments from different providers, the team communicates and works toward a common goal with the patient. The team may include physicians, psychologists, physical therapists, occupational therapists, nurses, pharmacists, dietitians, and other professionals, depending on the program. The focus is generally on helping people develop the skills and confidence to actively manage chronic pain and improve their ability to function. Treatment may include:
Programs are often intensive and may be group-based. Some hospital-based programs involve several hours of treatment each day for several weeks. The goal isn't simply to reduce pain. It's to help the person return to meaningful activities, improve physical and emotional functioning, reduce fear and avoidance, and become more confident in managing pain. This approach closely resembles the program I attended at Mayo Clinic. Mayo describes its Pain Rehabilitation Center as an integrated, team-based program that involves pain medicine, physical therapy, psychology, occupational therapy, biofeedback, and nursing, with a focus on self-management, physical reconditioning, medication management, and quality-of-life improvement. Why does the difference matter? When someone is referred to "pain management," it's reasonable to ask what that actually means. Will you primarily receive medications and procedures? Will you see several different specialists who work independently? Or will you participate in a coordinated rehabilitation program in which the team works together toward shared goals? None of these approaches is automatically right or wrong for everyone. The appropriate approach depends on the type of pain, the individual's medical situation, goals, and available treatment options. But for persistent chronic pain, particularly when pain has significantly affected physical function, emotional well-being, work, relationships, or quality of life — a comprehensive rehabilitation approach may offer something that a procedure-focused model can't: an opportunity to learn skills for managing pain over the long term. Active vs. passive pain management As pain becomes persistent, treatments aimed solely at reducing pain may not be enough. Medications, injections, procedures, and other symptom-focused treatments can have a role in appropriate circumstances. But they generally work best when they're part of a broader treatment plan that also helps the person become more active and develop self-management skills. The goal isn't to eliminate every passive treatment. The goal is to avoid becoming dependent on passive treatments as the only way to manage pain. An active self-management approach can help people develop the knowledge, skills, confidence, and physical capacity to take a more active role in managing their pain and their lives. My experience at Mayo Clinic It was my family doctor and a local surgeon who recommended that I attend the three-week outpatient Mayo Clinic Pain Rehabilitation Center rather than undergo another risky surgery in an attempt to fix my pain. The program changed my life. One of the most valuable parts of the experience was that I wasn't simply given another treatment and sent home. I learned how to approach pain differently. I worked with a team that addressed the physical, psychological, behavioral, and medical aspects of chronic pain. I learned about pain, participated in physical reconditioning, developed coping and self-management skills, and learned how my thoughts, emotions, behaviors, and activity levels could influence my experience of pain. Another important part of the program was social modeling—seeing other people with similar pain experiences work through the same challenges and develop the skills they needed to move forward. Mayo's current program continues to emphasize an integrated team approach, physical reconditioning, behavioral strategies, medication optimization, and support for people to shift toward greater self-management and a more active life. Conclusions and thoughts There isn't a single universal definition of “pain management,” and programs can differ considerably in their treatment philosophies, organization, and goals. When you're referred to pain management, don't be afraid to ask questions:
A comprehensive interdisciplinary pain rehabilitation program may not be the right choice for everyone. These programs can also be demanding, requiring a significant time commitment and active participation. But if you're living with persistent pain that has taken over your life, rehabilitation may offer something different from simply trying the next medication, procedure, or surgery. It can teach you skills that you can continue using long after the program ends. A final thought I believe the most important distinction isn't whether a program is called a pain clinic, pain center, pain management program, or pain rehabilitation program. It's this: Are you being given another treatment for your pain or are you also being given the tools and skills to manage your pain and take back your life? For me, learning to actively manage my chronic pain was a turning point. Please discuss your medical situation and treatment options with your healthcare team. Learn more
 Updated September 3, 2026 It's common for people living with chronic pain to talk about pain with family and friends. They may ask how you're feeling, whether it's a good day or a bad day, what treatments you've tried, or whether you're feeling any better. Talking about pain isn't necessarily a bad thing. Sometimes it's important and helpful. But when pain becomes the focus of many of our conversations, it can keep our attention centered on pain and make it harder to focus on the rest of our lives. When pain becomes the conversation People usually ask about the pain because they care about you. They want to know how you're doing and whether there's anything they can do to help. That's understandable. But when the same conversations happen day after day — How's the pain? What did the doctor say? Did the treatment help? How bad is it today? — pain can gradually become the center of your interactions with other people. You may begin to feel like your identity is becoming tied to the pain. The Institute for Chronic Pain describes this as "pain talk" — the persistent focus of conversations and attention on someone's pain. While this kind of attention is often well-intentioned, it can become unhelpful when pain occupies too much of everyone's time and attention. Your attention matters Pain naturally demands attention. When something hurts, it's difficult not to notice it. But attention can also work in the other direction. When we repeatedly focus on pain, talk about it, and monitor every change, we may reinforce the importance and threat we associate with it. Pain rehabilitation approaches therefore often encourage people to reduce unnecessary pain-focused attention and to redirect it toward activities, relationships, and goals that matter to them. This doesn't mean pretending the pain isn't there. It means recognizing it without continually making it the center of your attention. Change the conversation You don't have to participate in every conversation about the pain. If someone asks, "How's the pain today?" you can thank them for caring and then redirect the conversation. You might say: "I really appreciate you asking. I live with chronic pain, but I've learned to live well despite it, and I'd rather focus on something else. What have you been up to?" Or simply: "Thanks for asking. I'm doing okay. Let's talk about something more enjoyable." You're not denying your pain. You're choosing what you want the conversation—and your attention—to be about. Talk about pain when it matters Reducing pain talk doesn't mean you should stop communicating about pain altogether. There are times when talking about pain is important. If you develop a new symptom, experience a significant change, have concerns about a treatment or medication, or need help from your healthcare team, you should communicate those concerns. The goal isn't to stop talking about pain. The goal is to stop making pain the focus of everything. Make room for life I learned that I didn't have to constantly talk about pain to acknowledge that I was living with it. I could notice the pain without dwelling on it. I could acknowledge a difficult day without making the entire day about pain. And I could have conversations about family, friends, hobbies, goals, plans, and the things that make life meaningful. That's the shift I want to encourage. Don't let chronic pain take up more of your life than it already does Talk about the things you enjoy. Talk about the things you're looking forward to. Talk about the people and activities that matter to you. Fill your life with things that compete for your attention. You are more than the pain. A simple challenge The next time someone asks about the pain, try something different. Thank them for caring. Answer briefly if you need to. Then change the subject. Ask them about their family. Talk about something you're looking forward to. Discuss a hobby. Make plans. Laugh about something. Start making conversations about life — not just pain. I choose not to make chronic pain the focus of my everyday conversations. I still talk with my healthcare providers when something meaningful changes or needs attention, but I don't want pain to define every conversation or every day. I've learned that I can live with chronic pain without constantly talking about it. And for me, that has made a difference. Learn more Updated September 4, 2026
Chronic pain can affect much more than the body. It can influence thoughts, emotions, relationships, activities, and the way we see the future. Anger, resentment, frustration, and a sense of injustice can become part of the experience. At the same time, gratitude and forgiveness may offer opportunities to change how we respond to those emotions. They aren't magic cures for pain. But they may help reduce distress and suffering, improve well-being, and change the role pain plays in our lives. Forgiveness Living with chronic pain can sometimes leave us angry about what happened. Maybe an injury changed life unexpectedly. Maybe a medical treatment didn't work. Maybe something was missed or handled poorly. Maybe life simply feels unfair. I experienced that sense of injustice myself. Forgiveness doesn't mean that what happened was okay. It doesn't mean forgetting, excusing harmful behavior, giving up accountability, or reconciling with someone who hurt you. Forgiveness can mean letting go of some of the anger, resentment, and bitterness associated with what happened. Research on forgiveness and chronic pain is still limited, but a systematic review found that five of seven studies reviewed showed an association between lower forgiveness and either greater pain experience or lower pain tolerance. The authors concluded that more research is needed to determine whether forgiveness can be an effective intervention for chronic pain. (PubMed) The important question may not be: "Was what happened fair?" It may be: "Is continuing to carry this anger helping me move forward?" Sometimes letting go is less about changing what happened and more about changing what happens next. Gratitude Gratitude doesn't mean pretending everything is good. It doesn't mean ignoring difficult circumstances or telling yourself that you should be grateful because someone else has it worse. Gratitude means deliberately noticing and appreciating the things that are meaningful, helpful, or positive in life. Even when chronic pain is present, there may still be people, relationships, experiences, abilities, or moments worth appreciating. Research on gratitude interventions in the general population has found improvements in gratitude, mental health, anxiety, depression, life satisfaction, and positive mood, although the certainty of some findings is limited. (PMC) More recent research specifically examining fibromyalgia is also encouraging. A 2025 systematic review found that higher gratitude was associated with better quality of life, well-being, and some pain-related outcomes, but the authors emphasized that more research is needed before gratitude can be considered an established treatment. (PMC) Gratitude isn't about denying what is difficult. It's about making sure the difficult things don't become the only things that receive attention. Change the emotional experience Forgiveness and gratitude are two ways of changing how we respond emotionally to difficult circumstances. They don't require pretending that everything is okay. They require recognizing what we're feeling and deciding whether holding on to certain emotions is helping us or keeping us stuck. For me, learning to let go of some anger and resentment helped me move forward. Practicing gratitude helped me notice that chronic pain wasn't the only thing happening in my life. There were still people to love. Things to experience. Activities to enjoy. Goals to pursue. And reasons to be thankful. Try it yourself Consider starting with something simple. For forgiveness: Think about something that continues to generate anger or resentment. Ask yourself whether holding on to those emotions is helping you move forward. Forgiveness doesn't require forgetting or excusing what happened. It may simply mean choosing not to let the past continue to control the present. For gratitude: At the end of each day, identify three things you appreciated. They don't have to be significant. A conversation with someone you care about. A good meal. A beautiful day. A favorite song. A laugh. A walk.A good night's sleep. A moment when you accomplished something you didn't think you could do. The purpose isn't to convince yourself that life is perfect. It's to deliberately notice that life contains more than pain and problems. Let go and move forward Forgiveness and gratitude won't magically make chronic pain disappear. But they may help change how we experience difficult circumstances and how much attention we give them. Forgiveness can help us loosen the grip of anger and resentment. Gratitude can help us notice what remains meaningful and worthwhile. Neither requires denying reality. Both can help create space for something beyond pain. You don't have to forget the past to move forward. And you don't have to wait for everything to be perfect before finding something to appreciate. Sometimes moving forward begins with letting go of what no longer helps and making room for what does. Learn more about forgiveness
Learn more about gratitude
Learn more about anger management
Learn more about stress reduction Updated September 3, 2026
Some people with chronic pain find medical cannabis or cannabinoid-based products helpful, particularly for short-term symptom relief. However, questions remain about how effective these products are for chronic pain over the longer term, as well as their potential risks and side effects. Cannabis wasn't recommended by the Mayo Clinic when I attended its Pain Rehabilitation Center in 2018. The International Association for the Study of Pain (IASP) also does not currently endorse the general use of cannabis or cannabinoids for pain because it considers the available high-quality evidence insufficient. Importantly, IASP does not dismiss the experiences of people with pain who report benefit from these products. What does the research show? A systematic review and meta-analysis published in JAMA Network Open in 2022 examined 20 randomized clinical trials involving 1,459 people with clinical pain. The researchers found a substantial reduction in pain among people receiving placebo and didn't find a statistically significant difference between cannabinoid and placebo groups. This doesn't mean cannabis or cannabinoids can never help anyone. It means that, in the clinical trials included in this analysis, the evidence did not demonstrate a clear pain-relieving advantage over placebo. The findings also highlight an important issue in chronic pain treatment: expectations and the context surrounding a treatment can influence pain outcomes. This is one reason rigorous placebo-controlled research is important when evaluating treatments for chronic pain. The Problem With Passive Treatment Medication can be an important part of pain management for some people. But relying primarily on passive treatments can have a downside. When relief depends largely on a medication, procedure, or someone else providing the treatment, it can create dependence—not only on the medication itself, but also on the healthcare provider who prescribes it. Over time, this can reinforce the belief that pain relief depends primarily on something being done for you, rather than on your own ability to manage pain. This doesn't mean medication is inherently bad or that people should never use it. It means that medication works best as part of a broader approach that also helps people develop the knowledge, skills, confidence, and ability to manage pain themselves. Research on chronic pain self-management has identified an important distinction between passive and active approaches. Passive strategies, such as medication and rest, are common, while active strategies, such as exercise and behavioral or cognitive approaches, can help build self-management skills and self-efficacy. My Experience I have found that I don't need medication or supplements to manage my chronic pain. Of course, your experience may differ. Mine certainly did earlier in my pain journey. My relief came from changing how I think about, feel about, and behave around pain through pain rehabilitation and self-management. Instead of continually looking for something or someone to take my pain away, I learned skills that put more of the day-to-day management of my pain back in my own hands. That shift from passive treatment to active self-management was an important part of my recovery. It doesn't mean I believe everyone should stop taking medication or that medication has no place in chronic pain management. Different treatments work differently for different people, and decisions about cannabis, medications, or other treatments should be made with a qualified healthcare professional who understands your individual circumstances. The goal is not to eliminate every treatment that might help. The goal is to make sure that treatment supports your ability to manage your life rather than becoming the only way you believe you can manage your pain. The Bottom Line Medical cannabis and cannabinoid-based products remain an active area of research. Some people report meaningful benefits, but evidence for chronic pain remains mixed, and important questions remain about effectiveness, safety, appropriate products, dosing, and which people are most likely to benefit. IASP continues to call for more rigorous research into both potential benefits and harms. Rather than viewing cannabis as either a miracle treatment or something that can never help, it makes more sense to look at the evidence, understand the potential benefits and risks, and consider it as one possible component of an individualized treatment plan. For people living with chronic pain, self-management doesn't mean refusing medication or other treatments. It means developing the knowledge, skills, and confidence to play an active role in managing your pain and your life. That was an important part of my own pain rehabilitation—and ultimately helped me change the way I lived with chronic pain. Learn More
Learn more
Updated 09/3/2026
Did you know?
Back pain can be scary, especially when an MRI reveals an abnormality. But structural findings on a scan don't necessarily explain your pain, identify its cause, or mean that a specific treatment will help. Abnormal MRI findings are common in people without back pain, and they become more common with age. Disc degeneration, bulging discs, and other changes can appear on scans of people who have little or no pain. An abnormal MRI, by itself, does not tell you how much pain you should have—or necessarily what is causing it. Although persistent low back pain is common, a single specific structural cause cannot be identified in many cases. This doesn't mean the pain isn't real. Pain is a biopsychosocial experience, with biological, psychological, and social factors that can all contribute to how pain develops, persists, and changes over time. Fear of pain, stress, poor sleep, low mood, and avoiding movement can sometimes contribute to ongoing pain and disability. Understanding these factors can be an important part of learning how to manage back pain and move forward. The good news? Persistent back pain does not necessarily mean that your back is damaged, fragile, or wearing out. 10 Things Worth Knowing About Persistent Low Back Pain
When Should You Seek Medical Care? Most low back pain is not caused by a serious condition. However, some symptoms warrant prompt medical evaluation. Seek medical attention if back pain is accompanied by:
When in doubt, talk with a qualified healthcare professional who can evaluate your symptoms and help determine whether further testing is appropriate. The Bottom Line An MRI can show changes in your spine. It cannot tell you how much pain you should feel. Persistent back pain does not necessarily mean that your spine is damaged, fragile, or wearing out. Pain can be influenced by many interacting factors, and understanding these factors can change how you respond to pain. Movement is not necessarily the enemy. Pain does not always mean harm. And recovery is possible—even when pain has been around for a long time. The goal is not to ignore your pain. It is to understand it, respond to it differently, and gradually build your ability to live the life you want. Learn More
Research
Updated September 4, 2026
My article, published in HealthCentral (formerly Practical Pain Management), “We Have a Chronic Pain Problem, Not a Prescription Opioid Problem,” explored the benefits and risks of opioid therapy for chronic pain and the need for greater access to pain rehabilitation programs. Below is some of the original content I submitted that didn't make it into the published version. It provides additional context and explains how my own experience shaped my thinking about opioid therapy. The rise of prescription opioids Beginning in the 1990s, opioid prescribing for chronic noncancer pain increased substantially in the United States. Several factors contributed to this increase, including:
As opioid prescribing increased, so did opioid-related harms, including opioid use disorder and overdose deaths. The response eventually shifted toward reducing opioid prescribing and increasing awareness of the risks associated with long-term opioid therapy. That response was necessary. But some of the policies and practices that followed also created problems for people who were already taking opioids for chronic pain. What happened to patients taking opioids? Following the release of the CDC's 2016 opioid prescribing guideline, some patients experienced rapid or involuntary reductions in opioid doses, abrupt discontinuation, loss of access to prescribers, or inadequate support during tapering. Some people also struggled to find alternative treatments or access comprehensive pain rehabilitation. These experiences created fear and mistrust among many people living with chronic pain. It's important to distinguish those experiences from what the current CDC guideline actually recommends. The 2022 guideline specifically warns against abrupt discontinuation and rapid tapering and emphasizes individualized, patient-centered decisions. Rapid or abrupt discontinuation can cause withdrawal, worsening pain, psychological distress, and other serious problems. The FDA has also warned about harms associated with sudden discontinuation or rapid dose reductions in physically dependent patients. We need to learn from those experiences. Reducing inappropriate opioid use is important. But protecting patients from the harms of inappropriate tapering is important, too. Opioid therapy is not the same as addiction One thing that often gets lost in discussions about opioids is the distinction between physical dependence and opioid use disorder. A person who takes opioids regularly can develop physical dependence. That means the body has adapted to the medication, and suddenly stopping it can produce withdrawal symptoms. Physical dependence does not automatically mean that someone has an opioid use disorder. Someone can legitimately need help tapering from a medication without being addicted to it. That's one reason opioid treatment and opioid tapering need to be handled carefully and without judgment. Opioid therapy is a shared decision There isn't a crystal ball when it comes to pain treatment. There's no way to know with certainty how an individual person will respond to a particular treatment. For some people, opioid therapy may provide meaningful benefits that outweigh its risks. For others, the benefits may be limited, may diminish over time, or may not justify the risks. The decision should be individualized and made collaboratively by the patient and healthcare professional. Current CDC guidance recommends carefully weighing the benefits and risks of continuing opioid therapy. When benefits outweigh risks, clinicians should work with patients to optimize nonopioid therapies while continuing opioid therapy. When risks outweigh benefits, clinicians should work with patients to gradually reduce the dosage or discontinue opioids when appropriate. The goal shouldn't be to force everyone onto opioids or to force everyone off them. The goal should be appropriate, individualized care. What does the research show? A 2024 systematic review and meta-analysis examined 35 randomized controlled trials evaluating opioid therapy and quality of life in people with chronic noncancer pain. The researchers found statistically significant improvements in some physical measures of quality of life compared with placebo, but the effects were small and judged to be unlikely to be clinically important. They found no significant improvement in mental quality of life. The authors also noted that the evidence was low to medium quality and that the studies primarily examined the initial months of treatment. This doesn't mean opioids never help. It means we shouldn't assume that long-term opioid therapy will broadly restore quality of life for people living with chronic pain. Pain treatment needs to be about more than pain intensity. Function, activity, sleep, mood, relationships, quality of life, and the ability to participate in meaningful activities matter, too. Tapering can be difficult If a decision is made to reduce or discontinue long-term opioid therapy, tapering needs to be approached carefully. People may be afraid of increased pain, withdrawal symptoms, loss of function, or simply not knowing what will happen when their medication is reduced. Those concerns deserve to be taken seriously. The current CDC guideline recommends that tapering be individualized and developed collaboratively with the patient. It specifically advises against abrupt discontinuation and rapid dose reductions except in situations involving serious immediate safety concerns. Tapers may need to take months or longer, particularly after long-term opioid use. Patients need to understand that pain or other symptoms may temporarily worsen during a taper. Providers also need to understand that tapering isn't simply a matter of reducing a number on a prescription. The whole person needs to be supported. That means addressing pain, withdrawal symptoms, emotional distress, function, sleep, and access to appropriate nonopioid and nonpharmacologic treatments. Transitioning to self-management takes time One of the most important lessons I learned is that transitioning from reliance on treatment toward greater self-management doesn't happen overnight. It's a marathon, not a sprint. Pain rehabilitation can help people develop the knowledge, skills, confidence, and strategies they need to take a more active role in managing chronic pain. That doesn't mean refusing medication. It doesn't mean refusing medical care. And it doesn't mean that everyone needs to stop taking opioids. It means making self-management part of the overall treatment plan rather than relying on medical treatment to do everything for us. My experience My chronic pain recovery began when I accepted that pain was part of my life and stopped constantly searching for another doctor, procedure, or treatment that might finally make the pain disappear. Many thanks to the Mayo Clinic Pain Rehabilitation Center. Through pain rehabilitation, I learned how to self-manage my chronic pain and focus more on living my life than on constantly trying to eliminate the pain. As part of that process, I was able to taper off opioids — eventually stop other medications, including benzodiazepines, anticonvulsants, muscle relaxers, amphetamines, beta-blockers, antidepressants, and over-the-counter analgesics. I also moved away from other treatments that had become part of my previous approach to managing pain. That was my experience. I'm not suggesting that everyone with chronic pain should stop taking medication or follow the same path I did. What worked for me may not be appropriate for someone else. What I do believe is that people living with chronic pain should have the opportunity to learn active self-management skills and to participate meaningfully in decisions about their treatment. The bottom line Opioids are neither a miracle cure nor something that should automatically be dismissed. They can provide meaningful pain relief for some people, but they also carry important risks, particularly with long-term use. The answer isn't simply to prescribe more opioids. And it isn't simply to take them away. We need individualized, patient-centered care that considers both the benefits and risks of opioid therapy while also helping people develop active strategies for managing chronic pain. For some people, that may include continuing opioid therapy. For others, it may mean gradually reducing or discontinuing opioids. Either way, people shouldn't be abandoned. They should be supported. And they should have access to comprehensive pain care, including pain rehabilitation and self-management strategies when appropriate. For me, learning to actively manage chronic pain was a turning point. I stopped looking for someone to fix me and started learning how to live my life. That's the approach I believe deserves a bigger place in chronic pain care. Learn more
Updated September 4, 2026
Chronic pain can change your activities, routines, relationships, and expectations. It can also change the way you see yourself. You may find yourself focusing on what you can no longer do, comparing yourself with the person you were before chronic pain, or criticizing yourself when you have a difficult day. Don't. Pain can change what you do. It doesn't erase who you are. Be kind to yourself. What is self-compassion? Self-compassion means treating yourself with the same kindness, understanding, and patience you would offer someone else who was going through a difficult time. It doesn't mean feeling sorry for yourself. It doesn't mean making excuses. And it doesn't mean giving up. It means recognizing that you're dealing with something difficult without adding unnecessary self-criticism to the burden. Research on self-compassion and chronic pain is still developing. Studies suggest that self-compassion is associated with better psychological adjustment, self-efficacy, pain acceptance, and other outcomes, although the evidence isn't strong enough to say that self-compassion itself is a treatment for chronic pain. In other words, self-compassion isn't a cure for pain. It may be one way of changing how you respond to the challenges that come with living with pain. Give yourself some grace Living with chronic pain often requires adjusting expectations. You may not be able to do everything you once did. Your energy may vary from day to day. Plans may need to change. That's okay. Try to avoid judging yourself by what you could do before chronic pain. Instead, ask: What can I reasonably do today? Some days you may accomplish a lot. Other days, getting through the day may be an accomplishment in itself. Neither makes you more or less valuable. What you can do
Self-compassion doesn't mean avoiding challenges Being kind to yourself doesn't mean avoiding everything that's difficult. Sometimes self-compassion means resting. Sometimes it means asking for help. And sometimes it means gently challenging yourself to do something you've been avoiding because of fear, uncertainty, or low confidence. The goal isn't to make life smaller. It's to respond to yourself with understanding while continuing to move toward the life you want. Don't let pain define you One of the most important lessons I've learned is that chronic pain can become so dominant that we begin to see ourselves primarily through the lens of pain. But pain is something you experience. It isn't who you are. You are still a person with interests, relationships, strengths, experiences, values, goals, and things that matter to you. Don't lose sight of those things. Be patient with yourself. Be realistic with yourself. Challenge yourself when appropriate. And, above all, be kind to yourself. Try it yourself The next time you catch yourself being critical about something related to chronic pain, pause and ask: "What would I say to a friend who was going through the same thing?" Then try saying that to yourself. You may be surprised by how different the answer sounds. Learn more Updated September 4, 2026 Editor's note: This article is based on my experience and research. Everyone is different. Talk with your doctor or pharmacist before starting, stopping, or changing a supplement, especially if you take prescription or over-the-counter medications. Dietary supplements are everywhere. Many people living with chronic pain use vitamins, minerals, herbs, and other supplements hoping to reduce symptoms or improve their health. Some may be helpful for particular conditions or nutritional deficiencies. Others may provide little benefit, and some can cause harm. The important thing is not to assume that a product is safe or effective simply because it is labeled natural or sold as a dietary supplement. What you should know
The FDA recommends talking with a healthcare professional before using dietary supplements, particularly because supplements can interact with medications or medical conditions. Are supplements effective for chronic pain? There's no simple yes-or-no answer. Dietary supplements aren't one treatment. They include hundreds of different ingredients, and the evidence varies considerably. Some supplements have been studied for particular types of pain, but evidence for many products remains limited or inconsistent. For example, a systematic review of randomized trials examining dietary supplements for fibromyalgia found evidence of pain improvement, but no significant improvement in quality of life, and the authors called for better-designed studies. The important question isn't simply: "Is this natural?" Ask: "What evidence shows that this particular product helps people with my particular condition?" Can supplements become part of the pain cycle? Sometimes, the issue isn't just whether a supplement works. It's the role it plays in managing pain. If every increase in pain leads to another pill, product, treatment, or supplement, it's easy to become increasingly focused on finding something outside ourselves to make the pain better. That doesn't mean taking a supplement is inherently harmful or that medication has no place in pain management. It means it's worth asking: Is this treatment helping me become more confident and active in managing chronic pain—or am I becoming increasingly dependent on something outside myself to manage it? Active self-management doesn't mean refusing medication or other treatments. It means developing skills and strategies that allow you to play an active role in managing chronic pain rather than relying entirely on treatments to do it for you. My experience As part of the Mayo Clinic fibromyalgia program I attended, I met with a pharmacist to review the long list of prescription medicines, over-the-counter medicines, and supplements I was taking at the time. My medicine cabinet looked like a GNC store. I was instructed to bring the actual bottles to the appointment, so I packed them into a gym bag and took them with me. I was surprised as the pharmacist went through each bottle, making comments and recommendations about the products—including questions about product quality, labeling, ingredients, potential safety concerns, and dosing. By the end of the appointment, my list of medications and supplements was much shorter. She recommended that I stop most of the supplements I was taking. My gym bag was much lighter. That experience taught me an important lesson: More treatments don't necessarily mean better treatment. Sometimes the best approach is to step back, look at everything you're taking, and ask whether each one is actually helping. Before taking a supplement If you're considering a supplement for chronic pain, talk with your healthcare professional and consider asking:
A pharmacist can be particularly helpful when you're taking several medications and supplements. The bottom line Some supplements may be useful. Some may provide little or no meaningful benefit. And some can cause harm. Natural doesn't automatically mean safe, and available without a prescription doesn't automatically mean effective. Before adding another supplement to a chronic pain treatment plan, consider the evidence, potential risks, possible interactions, and whether you actually need it. Most importantly, don't let supplements, or any other treatment, become your only strategy for managing chronic pain. The goal isn't to find more things to take. The goal is to build the knowledge, skills, confidence, and strategies needed to live well while managing chronic pain. Review supplements with your healthcare team so you can make an informed decision. Learn more
Updated September 4, 2026 Our thoughts, emotions, and behaviors can influence how we experience and respond to pain. Cognitive Behavioral Therapy (CBT) is a form of psychological treatment that can help people identify unhelpful thoughts and behaviors, develop more effective coping strategies, and become more active in managing chronic pain. CBT doesn't mean that pain is "all in your head." The pain is real. Instead, CBT recognizes that pain is a complex biopsychosocial experience and that the way we think, feel, and behave can influence how we respond to pain and how much it affects our lives. How can CBT help? CBT is based on the idea that thoughts, emotions, behaviors, and pain can influence one another. When living with chronic pain, it's easy to become caught in unhelpful patterns. You may begin thinking:
Those thoughts can affect emotions and behavior. They may contribute to fear, avoidance, inactivity, frustration, or loss of confidence. CBT can help identify these patterns and develop more helpful ways of thinking and responding. The goal isn't to think just positively. It's about thinking more accurately and responding more effectively. CBT is about skills CBT can provide practical skills that you can continue using long after you've learned them. These may include:
These skills can help change the role pain plays in your life. CBT isn't about eliminating every unpleasant thought or emotion. It's about learning that thoughts are not always facts and that emotions don't have to determine what you do. CBT and self-management One of the things I value most about CBT is that it gives people tools they can use themselves. A therapist may teach you the skills, help you identify patterns, and provide guidance as you practice them. Over time, however, those skills can become part of your own self-management toolkit. That's important because chronic pain doesn't disappear when an appointment ends. You need strategies that you can use at home, at work, with family, and while doing the activities that matter to you. CBT can be one part of that toolkit. It isn't a cure for pain CBT isn't a magical cure for chronic pain. It doesn't mean pain is imaginary, and it doesn't guarantee it will disappear. The goal is broader than pain reduction. CBT can help people change how they respond to pain, reduce the impact of unhelpful thoughts and behaviors, improve coping and confidence, and work toward greater function and quality of life. Research supports CBT and other psychological approaches as useful components of chronic pain management, although the size of benefit varies among conditions and individuals. My experience I learned CBT while attending the three-week interdisciplinary Mayo Clinic Pain Rehabilitation Center. It changed my pain experience and my life by giving me practical tools to:
CBT didn't make my chronic pain disappear. It helped me change my relationship with pain and how I responded to it. That distinction was important. Find a therapist trained in CBT for chronic pain It can be difficult to find a psychologist or other mental health professional with specific training and experience in CBT for chronic pain. When looking for a therapist, ask about their experience working with people who have chronic pain and how they approach treatment. You may also want to ask how they incorporate pain education, cognitive restructuring, activity, goal setting, and self-management into their work. You can find search tools here:
Learn more and do more
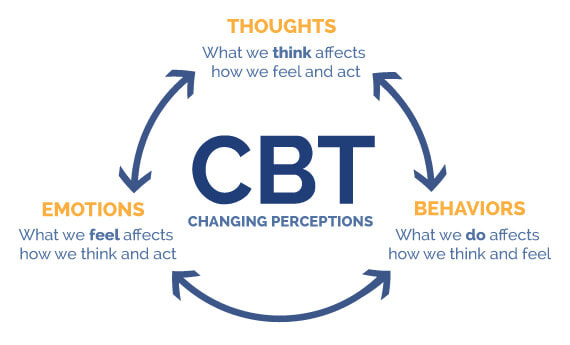 Image courtesy of McGovern Medical School
Updated September 4, 2026
Instead of starting your day believing you have a fixed number of spoons, consider what you can do throughout the day to support your energy, mood, confidence, and ability to participate in the things that matter. What is spoon theory? Christine Miserandino's spoon theory has become popular among people living with chronic illness and chronic pain as a way of explaining limited energy and planning how to use it. The basic idea is simple. You start each day with a limited number of spoons. Each spoon represents a unit of energy. As you use energy throughout the day, you use up your spoons. The metaphor can be helpful. It can encourage people to recognize their limits, plan ahead, prioritize important activities, and avoid overdoing things. But there can also be a downside. If we think of our energy as a fixed number of spoons that can only decrease throughout the day, we may begin to focus primarily on conserving energy rather than exploring what might help us feel more capable, engaged, or energized. What if energy isn't completely fixed? Our energy isn't simply a number that gets smaller every time we do something. How we feel can be influenced by many factors, including sleep, activity, mood, stress, expectations, social connection, and the activities we choose. That doesn't mean we can simply think ourselves out of fatigue or push through physical limitations. It means there may be opportunities to influence how we feel and function throughout the day. Sometimes doing something can actually make us feel better than doing nothing. A short walk may improve mood. Listening to music may help us relax. Talking with a friend may lift our spirits. Doing something enjoyable may take our attention away from pain. And successfully doing something we were afraid to do may increase our confidence. Watch for the inactivity cycle Research has found relationships among pain-related thoughts, activity, and sedentary behavior. In one daily-diary study of people with chronic pain, greater-than-usual pain catastrophizing in the morning was associated with more sedentary behavior and less moderate-to-vigorous physical activity that day. More sedentary behavior was, in turn, associated with greater pain catastrophizing the following morning. This doesn't mean that inactivity causes pain catastrophizing or that everyone should simply exercise more. It does illustrate how thoughts, behavior, and pain can interact in ways that may reinforce one another. Sometimes the strategy we use to protect ourselves from pain can unintentionally make life smaller. Don't confuse respecting limits with avoiding life There is an important difference between pacing yourself and avoiding activities because you're afraid they will use up your remaining energy. Pacing can help you balance activity and rest and avoid overdoing it. But if conserving energy means continually giving up activities that are meaningful to you, it may be worth reconsidering the approach. Ask: Am I protecting my energy or protecting myself from doing things because I'm afraid of what the pain might do? The answer may change from day to day. Sometimes rest is exactly what you need. Other times, doing something may help you feel better than expected. What can help? There is no magic way to recharge physical energy. But there are things you can do that may improve mood, reduce stress, increase confidence, support physical function, or make the day more meaningful. Consider experimenting with:
You don't have to do all of these. Experiment. Notice what helps. Think beyond the spoons The point isn't that spoon theory is wrong. For many people, it's a useful way to understand and communicate the challenges of limited energy. The point is that we don't necessarily have to think of our daily energy as a fixed number of spoons that can only disappear. Our capacity can change. Our mood can change. Our confidence can change. Our behavior can change. And sometimes, doing something rather than avoiding it can change how we feel. Respect your limits. Rest when you need to. But don't automatically assume that every limit you experience today will be the limit you have tomorrow. My experience I've learned that constantly thinking about what I have left in the tank can sometimes make me focus more on what I can't do. Instead, I try to ask: What can I do right now that might help me feel better, more engaged, or more connected to the life I want to live? Sometimes the answer is rest. Sometimes it's movement. Sometimes it's spending time with other people. Sometimes it's simply doing something I enjoy . The goal isn't to ignore limitations or push through everything. It's to find opportunities to participate in life rather than automatically assuming that pain or fatigue means I need to stop. The bottom line Spoon theory can be a useful tool for understanding limited energy and planning activities. But don't let the metaphor convince you that you have a fixed number of spoons that can only run out. Your energy and capacity can vary. Your mood can change. Your confidence can grow. Your abilities can change with practice and experience. And sometimes the best way to feel more engaged with life isn't to save another spoon. It's to use one. Note: This is simply another tool to add to your chronic pain toolbox. If spoon theory works well for you, there's no reason to stop using it. The goal isn't to replace one rigid rule with another; it's to find strategies that help you manage chronic pain while participating in a meaningful life. Updated September 4, 2026
People with chronic pain often fall into a "boom and bust" cycle. On a good day, we may try to catch up on everything we've been unable to do. We overdo it. Pain or other symptoms increase. Then we spend the next day — or several days — doing very little while we recover. Eventually we feel better, try to catch up again, and the cycle repeats. Pacing can help break that cycle What is pacing? Activity pacing is a way to balance activity and rest so we can participate more consistently in the things that matter to us. It may include:
Use pacing to move forward The goal of pacing shouldn't be to create a smaller and smaller life. It should be to help establish a consistent and sustainable level of activity. Once that level becomes manageable, we may be able to gradually increase what we do. For example, instead of walking until pain forces us to stop, we might set a manageable walking goal and practice it consistently. Over time, if that becomes easier, we can consider increasing the distance or duration. The same principle can apply to household chores, hobbies, exercise, social activities, or other meaningful activities. Pacing isn't the same as avoidance Chronic pain can cause us to become protective of ourselves. Pain is a warning signal, so it's understandable to avoid activities we believe will worsen it or cause further damage. But avoiding activity because of fear of pain can gradually make life smaller. We may stop exercising. Spend less time with friends. Give up hobbies. Avoid work or household activities. Or stop doing things we enjoy. Research has consistently found associations between activity avoidance and greater disability, pain, and psychological distress in people with chronic pain. These findings don't prove that avoidance causes those outcomes, but they do highlight the importance of avoiding unnecessary restriction of activity Ask yourself: Am I pacing so I can keep participating, or so I can avoid activity? That question can help distinguish pacing from avoidance. Pain doesn't always mean stop An increase in pain doesn't automatically mean that an activity has caused damage. For some people with chronic pain, movement or activity can be uncomfortable without being harmful. That doesn't mean we should ignore severe pain, new symptoms, or signs of injury. Nor does it mean we should push through everything. Instead, it means we can learn to distinguish between "This is uncomfortable" and "This is unsafe." That distinction can make it easier to stay active. The goal is progress, not perfection. Find your sustainable level There isn't one pacing formula that works for everyone. Your starting point depends on your current abilities, symptoms, goals, health, and circumstances. Start with something manageable. Be consistent. Then, when appropriate, gradually challenge yourself to do a little more. You don't have to wait until the pain disappears before you begin increasing activity. At the same time, you don't have to force yourself through every increase in pain. The goal is to find the balance between protecting yourself and challenging yourself . Keep moving forward Pacing can be a valuable self-management tool when it helps break the boom-and-bust cycle and maintain consistent participation in meaningful activities. Respect your limits. Take breaks when you need them. Modify activities when necessary. But also look for opportunities to expand what you can do. The evidence for pacing itself is still developing, and different pacing approaches may work differently for different people. A 2026 systematic review found that pacing interventions tended to improve function, but results for pain and fatigue were mixed, and confidence in the evidence was very low. That uncertainty doesn't mean pacing is useless. It means we should use it thoughtfully and focus on the outcomes that matter most. The bottom line Pacing isn't about avoiding activity. It's about finding a sustainable way to stay involved in life. Don't let a bad day convince you that you can't do anything at all. Don't let a good day convince you that you can do everything. Find a manageable starting point and stay consistent. And when you're ready, gradually move forward. The goal of pacing isn't to make life smaller. It's to make participation in life more sustainable. Learn more and do more
Updated September 4, 2026
I recently watched a great TEDx Talk by Dr. Trung Ngo about resilience that I think everyone who lives with or treats chronic pain should watch. In his talk, Dr. Ngo describes three ways people may respond to adversity:
I can identify with all three during my personal journey with chronic pain. When I felt like a victim Early in my journey, I felt like a victim. I believed the surgeon was responsible for my pain, and I was focused on making that doctor pay for his mistake and making the pain go away. I was angry, frustrated, and focused on what had happened to me. Those feelings were understandable. But eventually, I realized that continuing to focus on what I couldn't change wasn't helping me move forward. When I became a catastrophizer As the pain continued, my thinking became increasingly negative. It became gloom and doom. I became fearful of the pain. I worried about all the terrible things that might happen because of it. I worried about my future and my family's future. I began imagining the worst possible outcomes. Looking back, I can see how much of my life had become organized around pain and the fear of what might happen next. Becoming more resilient Fortunately, my mindset eventually shifted toward resilience. Many thanks to the Mayo Clinic Pain Rehabilitation Center for helping me make that transition. Resilience doesn't mean that pain isn't real or that difficult emotions disappear. It doesn't mean pretending everything is okay. For me, resilience meant learning that I could respond differently to the challenges chronic pain created. I could focus on what I could influence rather than spending all my energy on what I couldn't change. I learned to become more active in managing my life rather than waiting for someone else to fix me. That was a major turning point. How to be resilient According to Dr. Ngo, there are four important keys to resilience:
Resilience is a process I don't think resilience means that you never have a bad day, feel angry, become discouraged, or worry about the future. I still have difficult days. The difference is that I don't have to let those feelings determine what I do next. Resilience is the ability to adapt to difficult circumstances and continue moving toward a meaningful life. Sometimes that means pushing forward. Sometimes it means asking for help. Sometimes it means accepting that something cannot be changed and focusing your energy somewhere else. For me, resilience meant changing the question. Instead of continually asking, "How do I make this pain go away?", I began asking, "How can I live the life I want while managing this pain?" That change in perspective didn't make my pain disappear. It changed how I responded to it. What resilience taught me Chronic pain can affect much more than the body. It can influence our emotions, relationships, activities, expectations, and sense of who we are. Research has described chronic pain as an experience that can affect the whole person, not simply a physical symptom. That's one reason I believe resilience is so important. We may not be able to control everything that happens to us. We may not be able to control whether pain is present on a particular day. But we can work on how we respond. I learned that I didn't have to wait for pain to disappear before I started living again. I could build the skills and confidence to move forward with my life — pain included . The bottom line Resilience isn't about denying pain, thinking positively all the time, or doing everything on your own. It's about learning to adapt. It's recognizing what you can change, letting go of what you can't, accepting support when you need it, and continuing to participate in the things that give your life meaning. I spent years looking for someone to make my pain go away. Eventually, I learned that becoming more resilient wasn't about finding someone to fix me. It was about learning how to move forward. Learn more Pain doesn't have to determine your life.
I love this metaphor I first heard at the Mayo Clinic Pain Rehabilitation Center: Imagine being in a car with chronic pain. Where is the pain? Who's in control? Is pain behind the steering wheel - determining where you go and what you do in life? Or are you driving? Put pain in the back seat, or even better yet, the trunk. Things you can control - Focus on these
Things you can’t control - Don’t focus on these
My article originally published December 30, 2019 in National Pain Report. Edited March 16, 2023 Chronic pain appointments can be difficult for both doctors and patients.
For patients, doctor visits can be intimidating and create anxiety. We want validation of our pain, empathy, answers, and support. For doctors, chronic pain patients can be more challenging to treat than other patients. We can be demanding of their time, attention, and patience. While they genuinely want to help, doctors often have limited training (typically only 11 hours of pain education in medical school); limited time (typically only 15-20 minutes per appointment); limited options due to government, health system, and insurance guidelines; and limited internal resources to treat chronic pain patients. So how do you make the most of your appointment time and get the best treatment when you visit the doctor? Below are 25 suggestions to help maximize the patient-doctor experience (thanks to the many ideas provided by members of the Chronic Pain Champions – No Whining Allowed Facebook support group): In general
Before the appointment
At the appointment
Bottom line To get the best treatment from your doctor, be prepared, calm, engaged, insightful, and open to self-management. It’s harder for doctors to treat patients who are negative or expect the doctor to fix all their problems. I hope you find these tips helpful. Chronic pain can make it easy to feel overwhelmed, reduce our activity levels, and become isolated. Goals help restore a sense of order, build self-efficacy and sense of control, improve mood, and provide direction by helping with planning daily activities.
One of the tools we learned at the Mayo Clinic Pain Rehabilitation Center was goal setting to help us plan our days and keep us on track. We set goals each day. They didn't have to be massive, but they had to be SMART - specific, measurable, achievable, relevant, and time-bound.
Some SMART goal examples:
Did you notice none of the goal examples included pain reduction? Our focus should be on reducing stress, improving our quality of life and increasing functional ability and activity, not pain reduction. Focusing on pain reduction is an easy trap to fall into - leading to frustration and depression. Just as the homepage of my website says - we can live well, despite the pain. Celebrate! While it's natural to celebrate big goals, be sure to celebrate milestones along the way, as well as smaller victories. These celebrations keep us motivated along the way and help instill confidence. Resource Pain is the body’s alarm system. It’s designed to protect us from danger just like a home security system or a smoke detector. It’s the body’s normal response to acute tissue damage or injury and heals in normally 3-6 months.
But what happens when pain doesn’t go away? Once pain persists beyond the normal healing time, it becomes chronic - losing its warning function and becomes its own disease/condition. It’s an abnormal response (with or without obvious pathology). Although all pain hurts, not all pain indicates damage. We know what to expect from our pain by the very nature of it being chronic or ongoing. It’s not like getting burnt, twisting an ankle, or getting stung by a bee that needs protection until the injury has heals. Of course, any unexpected new pain should be investigated. Learn more
Pain, stress, and tension are closely related. Muscles tighten and put pressure on nerves resulting in even more pain.
It’s possible to activate your body’s natural relaxation response to help reduce the tension using mind-body tools like:
Helpful videos
Free Apps FIND MORE TOOLS AND APPS Updated 3/1/24 Pain rehabilitation goes beyond medicine and medical interventions – and crosses different disciplines. It doesn’t just focus on removing the pain. It focuses on the patient and how they can play a role in their own pain management - giving them control over the pain instead of letting the pain control them.. It’s a proven approach based on the biopsychosocial model of medicine – benefiting patients while reducing costs and reliance on the medical system. In addition to their general efficacy, these types of programs using interdisciplinary chronic pain rehabilitation can be effective at weaning patients off opioid therapy with long-term improvements in pain, mood, and function. I was fortunate to be able to attend the 3-week interdisciplinary Mayo Clinic Pain Rehabilitation Center – not just once, but twice. It was both a game-changer and lifesaver for me. I highly recommend the program to anyone interested in taking an active role in managing their own care. Read about my Mayo experience in this article. More programs like this are needed to shift the current reliance on biomedical therapy towards a greater reliance on provider-supported patient self-management and true biopsychosocial treatment. . Availability is important but so is accessibility. These programs aren't cheap, and insurance can be hesitant the pay the price tag. What payors need to remember is that these programs are cost-effective with a 68% reduction in medical cost spending. Find links to rehabilitation programs in the U.S. and around the globe. What to look for in a program A pain rehabilitation program should focus on you as a person, not just your pain. Interdisciplinary pain rehabilitation programs that take place in the same facility with health care providers working together with open communication and shared objectives are the gold standard of comprehensive care outperforming medical pain services and less coordinated multidisciplinary programs. A comprehensive pain rehabilitation program typically includes:
Learn more about pain rehabilitation
 Pro golfers use visualization when they play. They picture the precise shot they want to hit before taking the club back – the trajectory, shape, roll and finish. This puts a positive image in the mind; the body then makes the motions needed to turn the image into reality.
We can do the same with our pain. We can visualize a different way to view our pain and respond to it. We can visualize living well despite the pain. And we can visualize the pain leaving our bodies or the pain taking a smaller role in our lives. Try these exercises
Find links to these and other self-management tools. I was recently honored to be a guest on the Compass Opioid Stewardship Program podcast hosted by Dr. Rachael Duncan, PharmD. and Dr. Don Stader.
I'm so grateful for the opportunity and blessed to be able to share my story with clinicians. I'm also thankful for the generosity of Dr. Stader. You'll find out what he offered me at the end of the podcast. It brought me to tears. You can listen to the podcast episode on Apple, Spotify, and Libsyn via the links below: Check out the entire podcast series. Learn more about the Compass Opioid Stewardship Program. |